
Quick Clinical AnswerDisinhibited Social Engagement Disorder (DSED) is a trauma- and stressor-related pediatric condition defined by a profound absence of normal stranger anxiety. Children with DSED may inappropriately touch, follow, or leave secure areas with unfamiliar adults. The condition originates from severe pathogenic care, such as institutionalization or chronic neglect, which disrupts early neurobiological attachment. Evidence-based treatment requires family-focused dyadic therapy, not pharmacological intervention. Disinhibited Social Engagement Disorder (DSED) is a trauma- and stressor-related pediatric condition defined by a profound absence of normal stranger anxiety. Children with DSED may inappropriately touch, follow, or leave secure areas with unfamiliar adults. The condition originates from severe pathogenic care, such as institutionalization or chronic neglect, which disrupts early neurobiological attachment. Evidence-based treatment requires family-focused dyadic therapy, not pharmacological intervention. |
The Neurobiology of DSED and Pathogenic Care
To understand disinhibited social engagement disorder symptoms, one must examine the neurological impact of extreme early adversity. Healthy neurodevelopment relies on a secure caregiver-child dyad. When an infant experiences distress, a responsive caregiver regulates their nervous system, teaching the developing amygdala and prefrontal cortex to distinguish between safety and danger.
When an infant is subjected to “pathogenic care”, defined as chronic emotional neglect, high caregiver-to-child ratios in institutional settings, or the constant disruptions of the foster care system, this neurobiological blueprint fails to form. Landmark research, notably the Bucharest Early Intervention Project, demonstrated that extreme social deprivation physically alters brain architecture. The resulting attachment trauma leaves the child indiscriminately seeking physical and emotional connection from anyone, entirely bypassing the brain’s natural threat-detection systems.
Recognizing Symptoms Across Developmental Stages
DSED does not remain static; it morphs as a child’s mobility and social sphere expand. Early identification requires observing how these boundary deficits evolve across different developmental milestones, moving from passive acceptance of strangers to active, intrusive social behavior.
Infants and Toddlers (9 Months to 3 Years)
While neurotypical infants generally develop a healthy wariness of strangers around 7 to 9 months, infants at risk for DSED miss this milestone entirely. Instead of showing distress when separated from their primary caregiver, these toddlers will readily reach out to be held by unknown individuals in public environments. Furthermore, they fail to visually reference a trusted adult, a behavior known clinically as “checking back”, when exploring unfamiliar surroundings or facing new stimuli.

Preschoolers (3 to 5 Years)
As verbal and physical independence grows, the symptoms transition into highly intrusive social behaviors. Preschoolers with this condition frequently initiate inappropriate physical contact with strangers on playgrounds, demanding unprompted hugs or climbing onto a new adult’s lap. They will willingly hold hands and walk away with unknown individuals without seeking guardian approval. Additionally, they often engage unfamiliar adults with highly intimate, rapid-fire questions that violate standard cultural norms for their age group.
School-Age Children (6 to 12 Years)
In academic and structured peer environments, the lack of relational boundaries severely disrupts healthy socialization. School-age children may label recently introduced adults or peers as their “best friends” almost immediately. While they may exhibit a superficial charm, this frequently masks a profound inability to sustain reciprocal, deeply rooted friendships, leading them to manipulate classroom dynamics to secure constant, undivided attention from teachers or parent volunteers.
Adolescents (13+ Years)
Unresolved DSED in the teenage years frequently escalates into high-risk behavioral patterns. Adolescents demonstrate a dangerous lack of judgment regarding interpersonal boundaries and physical safety, often placing indiscriminate trust in predatory adults or high-risk peer groups. This period is heavily marked by severe friction with authority figures, as the teenager fundamentally misinterprets standard social boundaries as hostile rejection.
Clinical Diagnostic Benchmarks (DSM-5-TR)
Mental health professionals evaluate DSED using the framework established by the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (ICD-10-CM code F94.2). A clinical diagnosis requires evaluating the child’s behavioral profile alongside an extensive review of their early developmental history.
The assessment hinges on identifying a persistent behavioral pattern (Criterion A) where a child actively approaches and interacts with unfamiliar adults. This involves reduced reticence in approaching strangers, overly familiar physical or verbal behavior, a failure to check back with adult caregivers, and a willingness to depart with a stranger with zero hesitation.
Crucially, a clinician must confirm that these behaviors are not merely generalized impulsivity (Criterion B), but rather a specific deficit in social boundaries. The diagnosis strictly requires documented evidence of pathogenic care (Criterion C), such as chronic social neglect or institutional rearing, which is presumed to be the direct cause of the disturbed behavior (Criterion D). Clinicians will also note if the presentation is severe, or if the symptoms have been persistent for more than twelve months.
Differential Diagnosis: Isolating DSED
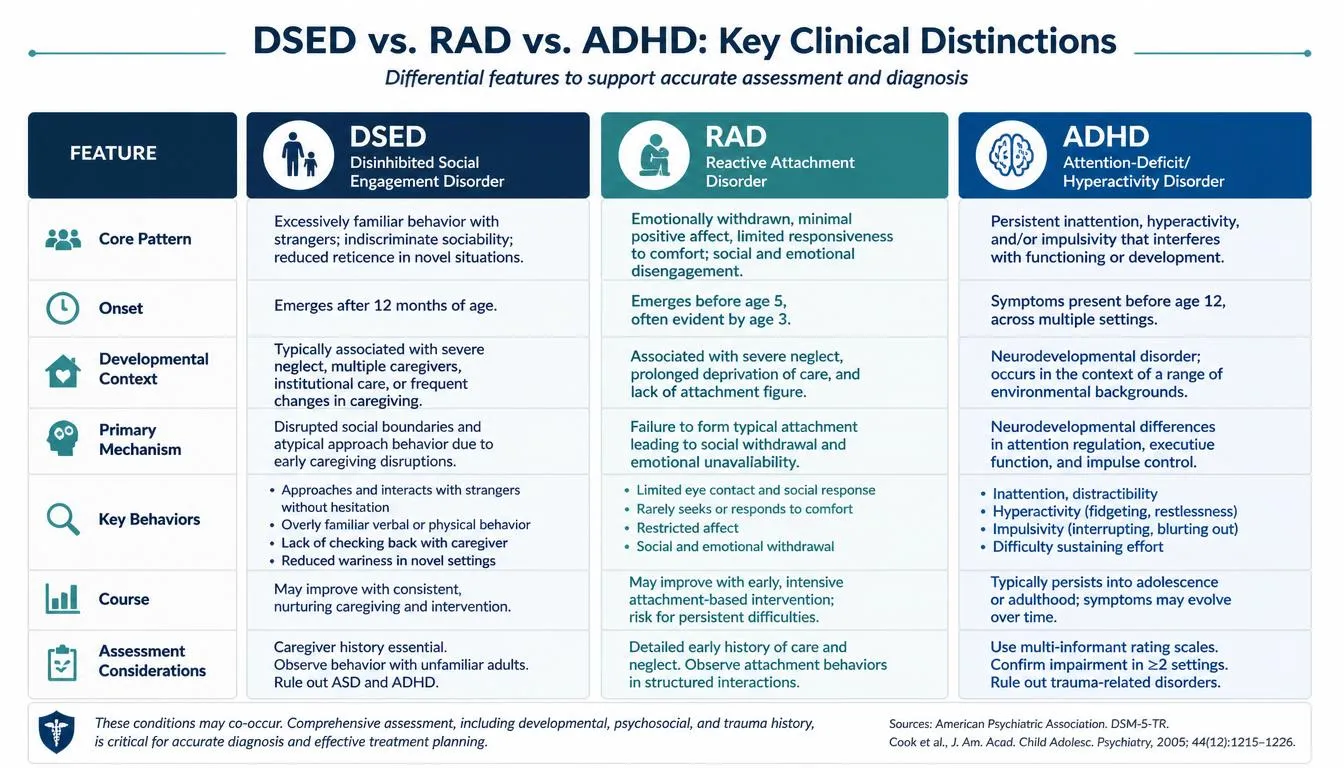
To isolate DSED effectively, clinicians must rule out other conditions presenting with hyperactivity or severe childhood trauma effects. This requires a precise differential diagnosis matrix.
|
Diagnostic Category |
Core Behavioral Presentation |
Primary Clinical Differentiator |
|
DSED |
Indiscriminate sociability, boundary violations, readily leaving with strangers. |
Driven by a desperate, dysregulated search for attachment following documented early neglect. |
|
Reactive Attachment Disorder |
Severe emotional withdrawal, flat affect, actively avoids caregiver comfort. |
While sharing the same root cause (trauma), Reactive Attachment Disorder (RAD) results in avoiding connection, not indiscriminately seeking it. |
|
ADHD |
Physical restlessness, impulsive interrupting, executive dysfunction. |
ADHD is neurological. Children generally maintain appropriate stranger anxiety and secure caregiver attachments. |
|
Autism Spectrum Disorder |
Missed social cues, atypical eye contact, specialized interests. |
Boundary crossings stem from neurodevelopmental communication deficits, unrelated to attachment trauma. |
|
Williams Syndrome |
Hypersocial behavior, highly verbal, distinct cardiovascular issues. |
A genetic condition (chromosome 7 microdeletion) requiring medical testing, not psychological trauma care. |
Evidence-Based Therapeutic Interventions
Pharmacotherapy is largely ineffective for the core symptoms of DSED. Healing the neurobiology of attachment requires dyadic therapeutic models that treat the parent and child simultaneously to rebuild the fractured foundation of trust.
Parent-Child Interaction Therapy (PCIT)
PCIT is an advanced modality where a therapist observes the caregiver and child interacting in a specialized playroom. The clinician provides real-time coaching to the caregiver via a discreet earpiece, helping them reshape the child’s dysregulated behavior at the exact moment it occurs. This live feedback loop enables the caregiver to establish themselves as a definitive, predictable anchor of safety.
Attachment and Biobehavioral Catch-up (ABC)
Tailored specifically for caregivers of infants and toddlers with high adverse childhood experience scores, the ABC program trains parents to interpret confusing behavioral cues accurately. Caregivers learn to override their own frustration or rejection sensitivity, providing overwhelmingly nurturing responses that gradually rewire the child’s dysregulated stress response system.
Structured Play Therapy
For preschool and early school-age children who lack the cognitive architecture to process complex emotions verbally, behavioral therapy for kids utilizes play as the primary communication language. Clinicians guide children through symbolic play scenarios to safely process early trauma, model appropriate physical boundaries, and practice emotional self-regulation techniques.
Trauma-Informed Caregiver Safety Protocols
Standard parenting advice is insufficient for managing the intense safety risks associated with DSED. Caregivers must deploy proactive, trauma-informed strategies to physically protect the child while long-term clinical therapy takes effect.
Deploy Redundant Safety Systems
Because the child lacks an internal threat detection system, parents must rely entirely on external fail-safes. This requires implementing robust physical tracking measures, such as securing GPS trackers within the child’s footwear and ensuring they wear medical ID bracelets containing emergency contact data. Dressing the child in highly visible neon clothing during outings to crowded public spaces also drastically reduces the time it takes to locate a wandering child.
Pre-Exposure Behavioral Scripting
Before entering high-risk, highly stimulating environments like public parks or shopping centers, caregivers must engage the child in behavioral roleplay. Parents should explicitly drill the rules using concrete language, teaching the child that while they may smile and wave at a new person, their feet must remain glued next to their parent, and they are strictly forbidden from asking strangers for physical affection.
The Physical Proximity Rule
Abstract commands like telling a child to “stay close” consistently fail because a child with DSED possesses a severely skewed definition of proximity and safety. Instead, caregivers must implement a strict “One-Arm Rule.” This creates a definitive, easily understandable physical boundary, requiring the child to remain within arm’s reach of the primary caregiver at all times in public spaces.

Educational Advocacy and Accommodations
DSED must be formally recognized and managed within the classroom environment. Caregivers should aggressively advocate for an Individualized Education Program (IEP) or a 504 Plan to legally mandate accommodations. Educators require specific training to recognize that the child’s intrusive charm or boundary crossing is a trauma response rather than mere friendliness, necessitating gentle but unyielding boundary enforcement throughout the school day.
Frequently Asked Questions
What is the main difference between DSED and RAD?
While both disorders stem from extreme early childhood neglect, they manifest in opposite ways. Reactive Attachment Disorder (RAD) causes a child to emotionally shut down and actively reject physical or emotional comfort. DSED causes a child to exhibit an indiscriminate, highly dangerous friendliness toward complete strangers.
Can an adopted child develop DSED?
Yes. DSED is disproportionately diagnosed in children who spent their critical early developmental periods in institutional care, such as orphanages, or who endured rapid, successive transitions within the foster care system prior to finding a permanent adoptive home.
Does DSED resolve on its own as the child grows up?
No. While the outward manifestation of the symptoms may shift as the child gains cognitive maturity, the underlying nervous system dysregulation persists. Without targeted, family-based clinical intervention, individuals remain at a high risk for chronic relationship instability, personality disorders, and substance misuse well into adulthood.
What is the most effective therapy for DSED?
The clinical gold standard involves dyadic therapies that work with the parent and child together. Parent-Child Interaction Therapy (PCIT) and Attachment and Biobehavioral Catch-up (ABC) are highly effective because they bypass traditional talk therapy, focusing instead on actively rebuilding the fractured attachment bond in real-time.
Medical Disclaimer & E-E-A-T AttributionThis article is for educational purposes and does not replace personalized medical or psychological advice. If you are recovering from a brain injury, trauma, or a mental health condition, work with a licensed clinician to build a plan suited to your situation. Written by: Adil Farooq, Psychiatry Magazine Medically reviewed by: [Dr. Adil Farooq MS · PhD] · Updated: 2026 |


